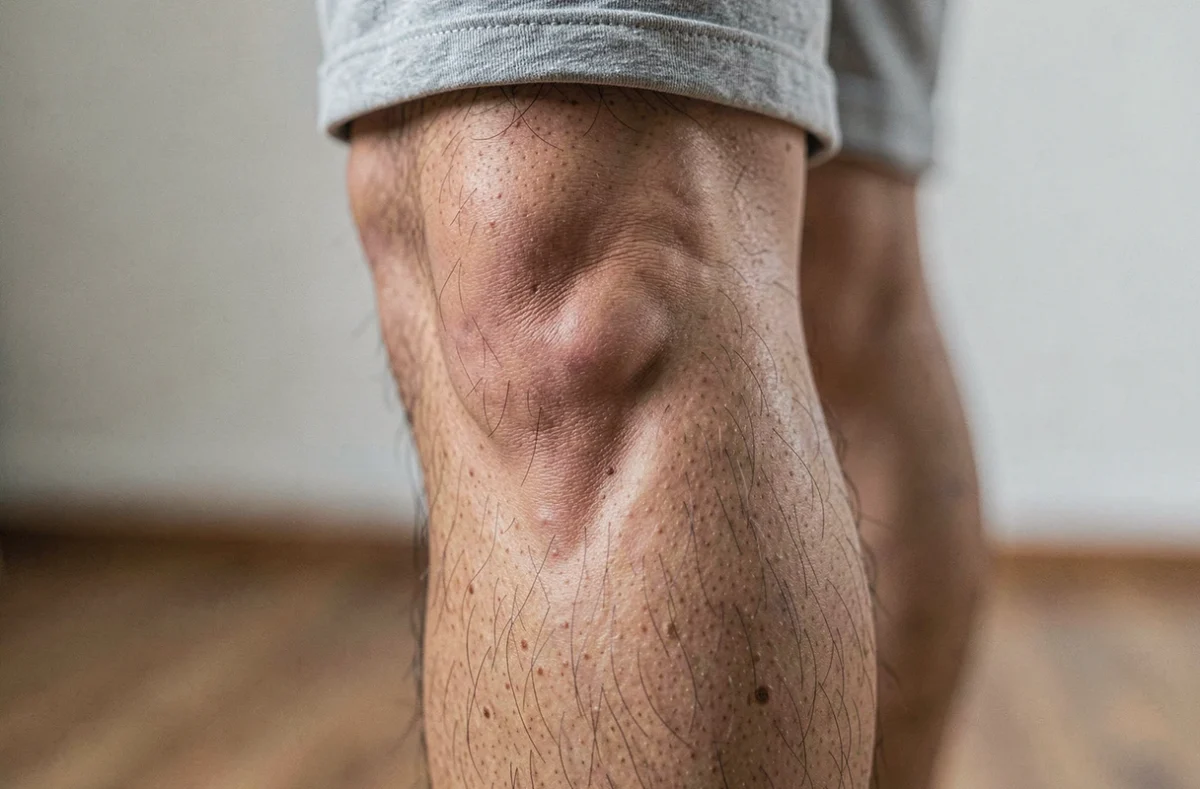
A swollen knee at the back, a feeling of tension in the popliteal fossa when bending the leg: the Baker’s cyst often manifests this way. This pocket filled with joint fluid, also called a popliteal cyst, affects a significant proportion of people who undergo a knee MRI. Most of the time, one lives with it without knowing. The problem begins when certain signals change in nature or intensity.
Rupture of the popliteal cyst and risk of confusion with thrombosis
The most misleading situation on the ground is the rupture. The joint fluid spreads into the calf tissues, and within a few hours, one finds themselves with a swollen, warm, painful leg, sometimes with a bruise that descends toward the ankle.
The picture almost resembles that of deep vein thrombosis. The two situations cannot be reliably distinguished at home. Neither the location of the pain nor the intensity of the swelling allows for a clear decision without imaging.
This is why a sudden calf pain associated with unilateral swelling justifies a consultation on the same day. The doctor will refer for a Doppler ultrasound to rule out thrombosis before concluding a cyst rupture. You can see the advice from Bien et Vous to better understand the situations that warrant a quick evaluation.
Waiting for “it to pass” in this specific case exposes one to a delay in diagnosis if it is indeed a clot. The reflex to remember: swollen calf on one side, consultation within the day.
Knee or calf swelling: what the location reveals
Not all swellings around the knee are the same. The affected area gives a first practical indication of what is happening underneath.
A swelling limited to the knee joint, with a soft and normal-looking calf, points more towards a classic joint problem: effusion related to osteoarthritis, inflammatory flare-up, stable popliteal cyst. This profile does not constitute an emergency but deserves a scheduled medical opinion if discomfort persists.
On the other hand, a swelling that extends to the calf, ankle, or the entire leg changes the situation. This type of presentation may correspond to a cyst rupture, deep vein thrombosis, or an infection. The urgency is more pronounced, especially if the swelling appeared quickly and affects only one side.
Warning signs to spot on the ground
- A tense calf, warm to the touch, with pain that increases when placing the foot flat: do not wait to consult, even if one thinks of the cyst
- A redness that gradually spreads along the leg, sometimes accompanied by fever: this picture suggests more of an infection than a simple ruptured cyst
- A knee locked in flexion, impossible to fully extend, with marked swelling in the popliteal fossa: the volume of the cyst may compress nearby structures
These distinctions do not replace imaging. They serve to calibrate the degree of urgency before accessing the doctor.
Respiratory signs associated with a swollen leg: when to call emergency services
This scenario is rarely discussed in articles about the knee cyst, but it exists. Sudden shortness of breath, chest pain, malaise, or coughing up blood, combined with a painful or swollen leg, constitutes an absolute emergency.
These symptoms may correspond to a pulmonary embolism. The mechanism: a clot formed in the leg migrates to the lungs. It is not the cyst itself that causes the embolism, but the venous thrombosis that may coexist with it or be confused with its rupture.
In this case, one does not schedule an appointment. One calls 15 or goes to the emergency room. The speed of care makes all the difference in prognosis.
Baker’s cyst and knee osteoarthritis: treat the cause rather than the bump
The popliteal cyst is rarely an isolated problem. In most cases, it is the consequence of an underlying joint disorder. Knee osteoarthritis is the most frequent cause in people over fifty. Meniscal injuries and chronic joint inflammation also contribute to the excessive production of synovial fluid that fills the cyst.
Draining the cyst without treating the underlying joint cause often leads to a recurrence. The fluid reforms because the joint continues to produce an excess of synovial fluid in response to irritation or wear.
What concretely reduces the volume of the cyst
Management primarily relies on treating the underlying joint pathology. When osteoarthritis is stabilized or the meniscal injury is corrected, the cyst decreases or disappears in many cases.
Targeted muscle strengthening (quadriceps, hamstrings) helps better distribute the stresses on the joint. Ultrasound-guided drainage can provide temporary relief if the cyst is very large and hinders mobility. Surgery remains reserved for recurrent or compressive cysts after failure of other approaches.
The popliteal cyst is a joint symptom, not an autonomous disease. This logic guides the diagnosis and treatment choice by the doctor.
Monitoring a knee cyst is primarily about monitoring what happens around it: joint mobility, the appearance of new swellings, the response to background treatment. A stable and painless cyst often requires no intervention. However, a cyst that suddenly changes in size, accompanied by calf pain or general signs, requires a rapid evaluation to rule out complications that do not wait.


